Vertebroplasty

Vertebroplasty for compression fractures · St. Louis

Vertebroplasty For Compression Fractures

Vertebroplasty treats a painful spinal compression fracture. Medical-grade bone cement goes through a needle into the broken vertebra. The cement hardens within 15 minutes, like an internal cast. It is for fractures, most often from osteoporosis, that have not responded to pain medicine. Patients typically go home the same day.

Take the first step toward relief. Complete the form, and we’ll reach out to you for a confidential discussion about your needs.

Prefer not to fill in a form?

Same-day and emergency appointments are available.

What is vertebroplasty?

Bed rest and strong pain medicine are no longer the only treatments for back pain caused by compression fractures of the spine. Now there is a breakthrough, minimally invasive procedure called percutaneous vertebroplasty. It uses bone cement to fill the spaces in a broken or crushed vertebra.

Vertebroplasty is a pain treatment for vertebral compression fractures that do not respond to standard care. Pain pills may give little or no relief. Or the narcotic doses needed are intolerable.

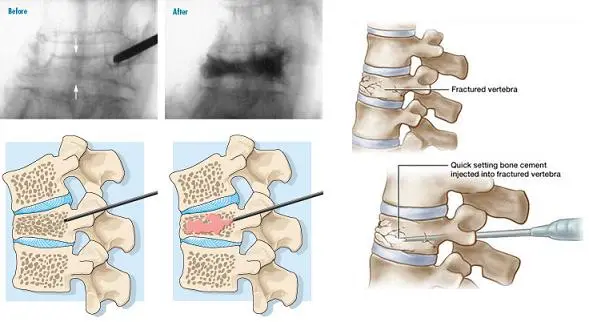
Vertebroplasty stabilizes the collapsed vertebra with the injection of medical-grade bone cement into the spine. This reduces pain. It can also prevent further collapse of the vertebra. That prevents the height loss and spine curving so often seen with osteoporosis. Vertebroplasty dramatically improves back pain within hours of the procedure. Multiple studies have shown it gives long-term pain relief and has a low complication rate.

Percutaneous vertebroplasty strengthens the treated vertebra and gives pain relief in most patients. The term “percutaneous” means injecting a fluid through a needle. “Plasty” means to mold or form. So vertebroplasty helps mold the vertebrae by injecting a fluid into the bone.

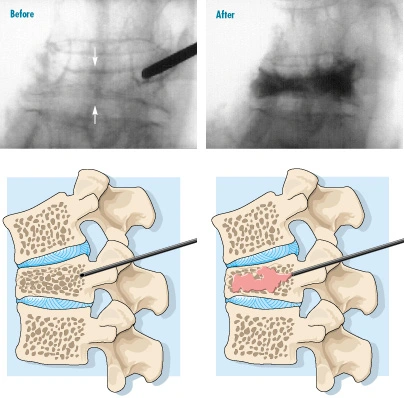
In this case, the doctor injects a bone cement mixture into the vertebral body. It contains polymethylmethacrylate, the same cement used in joint replacement surgery. It also has barium or tantalum powder, which makes the cement show up on X-ray. An antibiotic and a solvent round out the mix. The cement hardens within 15 minutes and stabilizes the fracture, like an internal cast.

Vert Thoracic Vertebroplasty Anatomy02
Vertebroplasty Large

What is a spinal compression fracture?

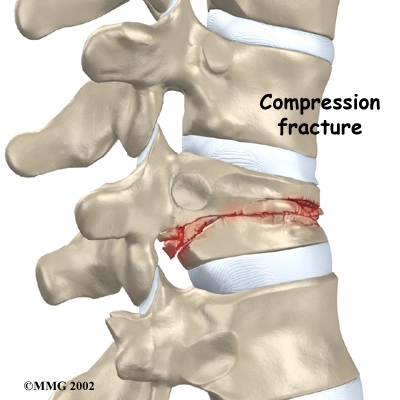
Vertebrae are bones that form a flexible column to protect the spinal cord. A compression fracture happens when a vertebra breaks or is crushed. When this happens, a person can feel extreme pain that may last a lifetime. Often the pain keeps the person from normal activities. Certain cancers, benign (non-cancer) tumors, or osteoporosis of the spine can cause compression fractures.

Osteoporosis is the loss of bone mass. It is the most common cause of compression fractures. It is the most common cause of vertebral compression fractures in the United States. The National Osteoporosis Foundation (NOF) estimates that over 50 million Americans over the age of 50 have osteoporosis. Or they have low bone mass with serious risk of osteoporosis.

A large part of this group will suffer disabling pain from vertebral compression fractures. It is most often found in women after menopause. Certain medicines or diseases can also cause it. Nearly all vertebral fractures in otherwise healthy people are due to osteoporosis. In people with this bone-weakening disease, they can happen from a minor impact, such as a bump or a fall.

People who have a spinal fracture often don’t realize they may have osteoporosis. That is because the disease causes no symptoms until a fracture occurs. Many patients with compression fractures caused by osteoporosis can be helped with this procedure.

Back Pain Round Imgages

Restore Stability In Your Spine With Vertebroplasty

Contact us now to schedule a consultation. See how Vertebroplasty can restore stability and ease your pain.

Factors that increase the likelihood of developing osteoporosis include:

  • Being female
  • Being thin or having a small frame
  • Advanced age
  • A family history of osteoporosis
  • Being past menopause
  • Abnormal absence of menstrual periods
  • Anorexia or bulimia
  • A diet low in calcium
  • Long-term use of drugs such as corticosteroids or anticonvulsants (seizure drugs)
  • Lack of exercise
  • Smoking
  • Heavy use of alcohol

Bone tumors and metastatic bone disease (cancer that has spread to bone) also lead to vertebral compression fractures. Diseases such as multiple myeloma and hemangioma (types of tumors) put patients at great risk for these painful fractures. High doses of steroids can also raise the risk of low bone mass and fractures. Those steroids are used to control auto-immune diseases such as lupus and rheumatoid arthritis, as well as asthma or chronic lung disease.

Percutaneous vertebroplasty may be done as an inpatient or outpatient procedure. It depends on how bad the fracture is and the health of the patient. After mild sedation is given, a needle is placed into the affected vertebra. The damaged area is then filled with bone cement.

Is vertebroplasty safe?

In many patients, the pain is lessened or even gone within 24 hours. There are few side effects or problems. In some cases, increased pain and fever may occur for a short time. This is treated with anti-inflammatory drugs. Other risks include infection and allergic reactions to x-ray dye or other medicines. There is a very small risk that the cement could leak outside the vertebra during the procedure. That could cause spinal cord or nerve damage.

If leakage occurs, surgery could be required and the patient could have permanent nerve and organ injury.

Pre-Operative Preparation

For proper and thorough treatment, review your current medical history with your physician. Your physician may ask you to change your current medication schedule. Tell your physician if you take blood thinners or have a history of a bleeding disorder. Also tell them if you are allergic to any medications or have an infection anywhere in your body. Rest well the night before the procedure. Patients having outpatient surgery are routinely asked not to eat the night before. You will get a mild sedative during the procedure. So you will probably be asked to have someone drive you to and from the medical facility. If you are on Coumadin, Heparin, Plavix or any other blood thinners (including Aspirin), or the diabetic medication Glucophage, you must notify this office. We will explain the timing of these medications. You will be at the clinic facility or hospital for about 2-3 hours for your procedure. You will need to bring a driver with you.

Vertebroplasty Xray
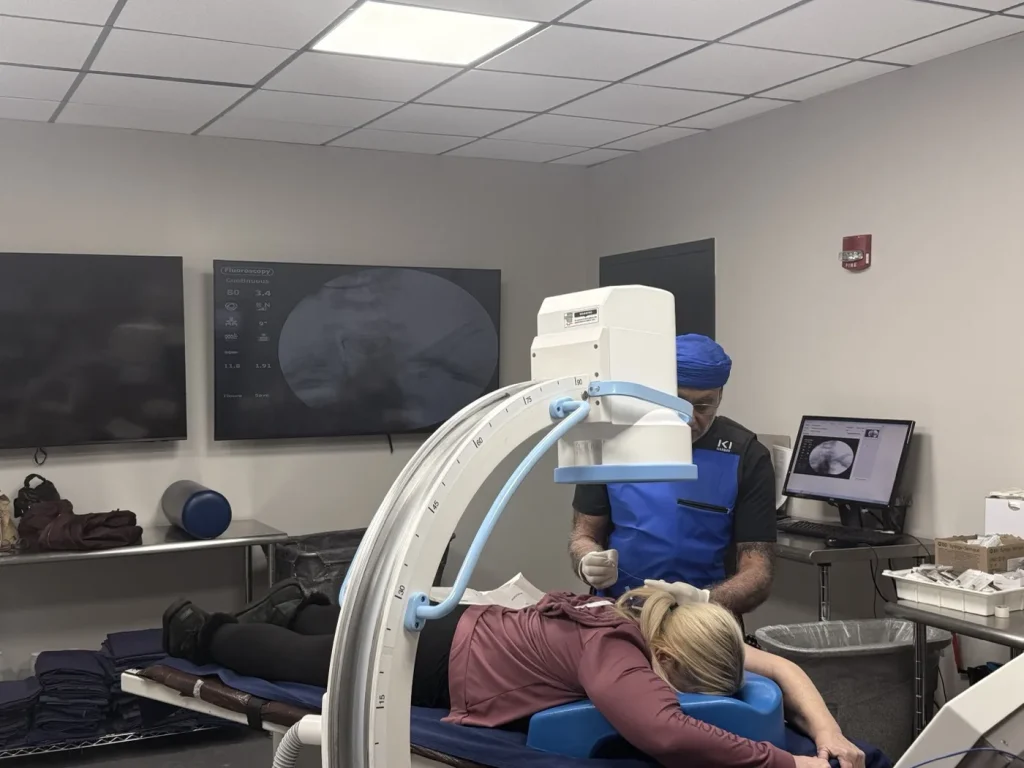
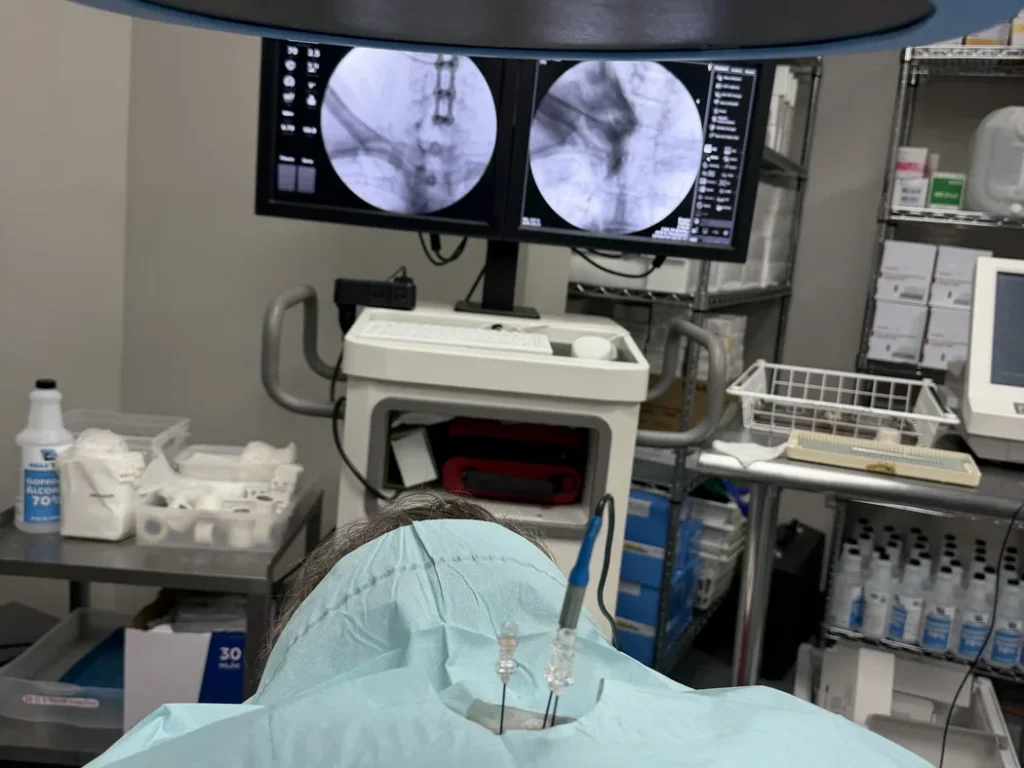
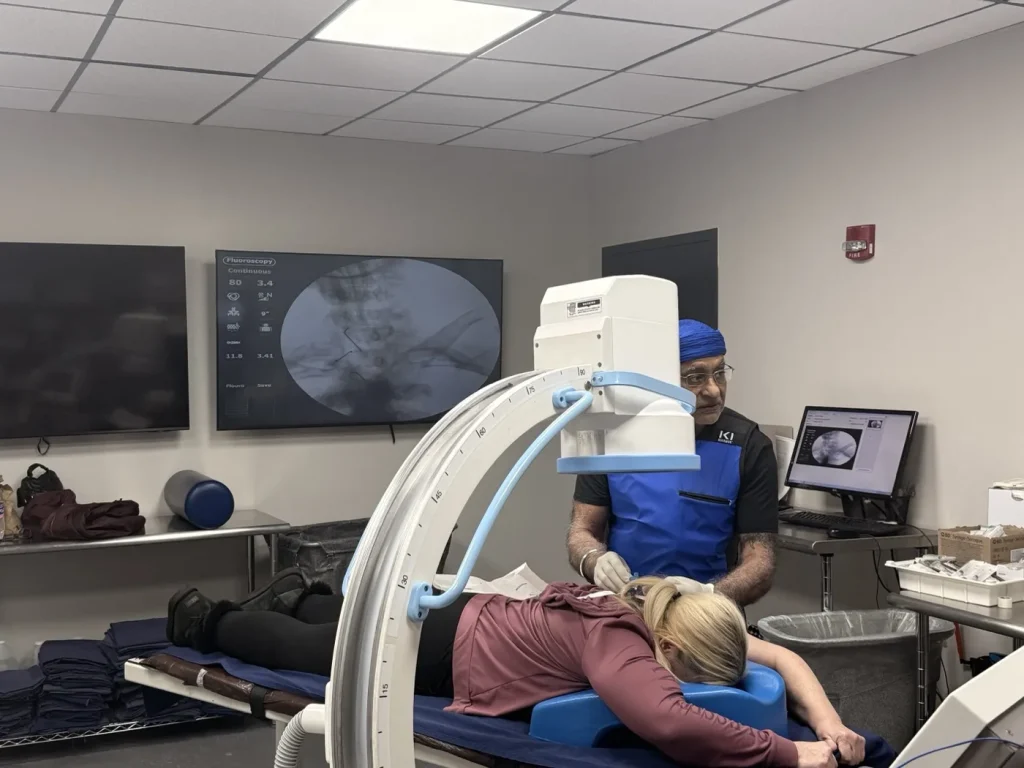
The bone cement is a plastic paste, similar to glue used to hold artificial joints in place. The cement holds the fragile bones in place making the vertebra stronger. A special imaging machine that allows the pain doctor to see the exact placement of the needle throughout the procedure. It also shows the cement as it fills the vertebra.

What happens during and after vertebroplasty?

During the Procedure

It is standard to have an IV needle placed in your arm and to get a light sedative. Once you are in position on the operating table, your back will be numbed with a local anesthetic. Under x-ray guidance, your physician will place an access needle into your vertebral body. You may feel mild discomfort during this part. When the cement is injected, your regular back pain will briefly return.

After the procedure

You must lie flat after the procedure. You will need a follow-up visit in the clinic after five to ten days. Keep the area clean and dry to help prevent skin infection. Do not do any heavy lifting for 3 months (that is, nothing heavier than a carton of milk). After that, you can slowly increase your lifting to normal. Walking is encouraged, and you can bend within the limits of your brace. You may feel some muscle soreness where the needles were placed. A mild pain reliever such as Tylenol can treat this. Do not drive for the rest of the day. Please have an adult drive you home or ride with you in a taxi or other public transportation. Depending on how you feel, you may return to normal activities and work the next day.

Benefits: Immediate Relief from Pain, Improved Quality of Life

After vertebroplasty, most patients (>90%) find a marked improvement in their pain. Mobility and quality of life improve too. Within a few days, many patients can reduce their pain medications significantly. They return to the daily activities their painful vertebral compression fractures had blocked. Most patients report lasting pain relief, even years later.

What are the risks of vertebroplasty?

The risks are minimal. In fact, few complications have been reported, involving less than five percent of cases. As with any procedure, there is a risk of significant complications. The most common side effects from the nerve root block can include (but are not limited to):

  • Allergic reactions to medications.
  • Infection (occurs in less than 1 per 15,000 injections).
  • Post-injection flare (nerve root irritation with pain several hours after treatment, which may last days or weeks).
  • Depigmentation (a whitening of the skin).
  • Local fat atrophy (thinning of the skin).
  • Destruction of a motor or sensory nerve in the path of the needle.
  • Bleeding, nerve injury, organ injury and death are rare but possible.
  • Cement leakage is possible.  The cement used in vertebroplasty is a liquid. It is squeezed into the fractured vertebra under high pressure. Some of the cement commonly leaks out of the vertebra, but this usually doesn’t cause any problems. Only rarely does a cement leak press on the spinal cord or nearby nerves. In these cases, surgery may be needed to remove the pressure.
  • Ongoing pain may occur. Many patients get nearly complete relief of symptoms from vertebroplasty. As with any procedure, though, you should expect some pain afterward. If the pain continues or becomes unbearable, talk to your doctor about treatments that can help control your pain.
What Our Patients Say

Individual results vary. These are unpaid patient testimonials shared with permission and are not a guarantee of outcome. See all patient stories.

Vertebroplasty FAQs

Both stabilize a fractured vertebra with bone cement. Kyphoplasty adds a balloon step first. It creates a cavity and, where the fracture allows, restores some lost vertebral height. Vertebroplasty injects cement without that step. Which one fits depends on the age of the fracture and how much it has collapsed.

Many patients notice meaningful improvement within a day or two. That is when the cement sets and the vertebra stabilizes. Response varies with the age of the fracture and the number of levels treated.

Yes, and this matters. A first compression fracture substantially raises the risk of another. Vertebroplasty stabilizes the bone that is already broken. It does not strengthen the bone around it. Checking and treating the underlying osteoporosis is an essential part of care, not an optional extra.

Yes. It is minimally invasive and done under image guidance with local anesthetic and mild sedation. Patients typically go home the same day. You will need someone to drive you.

Fractures that have already healed in a collapsed position generally do not respond. That is why we use MRI to check whether a fracture is still active before recommending the procedure. Timing is the single biggest factor in whether it helps.

You get a light sedative through an IV, and your back is numbed with a local anesthetic. You may feel mild discomfort while the access needle is placed. Your usual back pain briefly returns while the cement is injected. Afterward, some muscle soreness where the needles went in is common. A mild pain reliever such as Tylenol usually handles it.

Side effects are few, but they are real. Some patients have a short spell of increased pain and fever, treated with anti-inflammatory drugs. Infection and allergic reactions to X-ray dye or other medications are possible. There is a very small risk that cement leaks outside the vertebra and presses on the spinal cord or nerves. If that happens, surgery may be needed to relieve the pressure.

In many patients, the pain is lessened or gone within 24 hours. You lie flat after the procedure, and someone else drives you home. You can return to normal activities and work the next day if you feel up to it. Walking is encouraged. No heavy lifting for three months, nothing heavier than a carton of milk. Plan a clinic follow-up in five to ten days.

It is for painful compression fractures that have not responded to standard treatment. That means pain medicine gives little or no relief, or the narcotic doses needed are intolerable. Osteoporosis is the most common cause. Bone tumors such as multiple myeloma and hemangioma can also cause these fractures. The fracture needs to still be active. One that has already healed in a collapsed position generally does not respond.

Send A Message

For questions and concerns, please fill out the form below.

Prefer not to fill in a form?

Same-day and emergency appointments are available.

Pain Conditions We Treat​

At Padda Institute, our pain management specialists & pain specialist doctors provide you the guidance and treatments tailored to your needs. We are best at what we do; we diagnose and evaluate to determine your best treatment plan, so that you can experience chronic pain relief like never before.

Selective Nerve Root Block

Nerve roots exit your spinal cord and form nerves that travel into your arms or legs. These nerves allow you to move your arms, chest wall, and..

Discogram

The disks are soft, cushion-like pads that separate the hard bones of your spine. A disk may be painful when it bulges, herniates..

Epidural Steroid Injection (ESI)

Back pain affects nearly everyone at some point in their adult life. Often the exact cause of pain is not easy to see, as there are many..

Schedule NowCall (314) 481-5000