
Fall-risk balance testing · St. Louis
VNG balance testing plus brain, gait, sensation, blood flow and nerve tests. We find which system is failing and how much reserve is left. No referral needed.
Prefer not to fill in a form?
Same-day and emergency appointments are available.
Standing upright is not one system. It is three, checking each other several times a second. One is the balance organ of the inner ear. One is the sense of position coming up from your feet and legs. One is vision. The brain compares the three. When they agree, you do not think about it. When one drifts and the other two disagree, you feel unsteady. Then you make up for it, usually without knowing.
Videonystagmography — VNG — measures the first of those three directly. Small sensors around the eyes record eye movement. You follow targets, change head position, and sit in the dark. Why the eyes? The inner ear is wired straight to the muscles that move them. That reflex holds an image steady while your head moves. Recording the eyes is the most practical way to read an organ buried in bone.
What comes back is not a yes or no. It tells us which side is weaker. It tells us if the loss is in the ear itself (peripheral) or in the brain (central). And it shows how much of your balance now rests on vision and your feet — the two systems that cover when the inner ear stops pulling its weight.
Because the people most likely to have two of the three systems failing at once are the people we see every day.
Peripheral neuropathy (nerve damage in the feet and legs) takes away position sense from the feet. Cervical radiculopathy (a pinched nerve in the neck) and spinal stenosis change how the legs fire. Chronic pain cuts how much people move, and movement is what keeps balance. Several drug types used for pain and blood pressure blunt the reflexes that catch you. Diabetes damages nerve, vessel, and — as the data below show — the inner ear too.
A patient with numb feet has already spent their reserve. They are standing on vision and the inner ear. If the inner ear is also failing and nobody has checked, the first sign is the fall.
This part changes care, so we will state it exactly.
Using the National Health and Nutrition Examination Survey, Agrawal and colleagues found that 35.4 percent of US adults aged 40 and older — about 69 million people — had measurable vestibular dysfunction (inner-ear balance loss). Odds were 70 percent higher in people with diabetes. Some of them had symptoms, meaning they reported dizziness. In that group the odds of falling rose twelvefold. That is a survey of 5,086 US adults aged 40 and older. The measure was a standing-balance test, not a full set of inner-ear tests.
A second analysis of the same survey went further. It asked the question that matters here. In a person with diabetes, is the inner-ear problem just the neuropathy showing up again, or is it its own thing? Vestibular dysfunction independently raised the odds of falling more than twofold — odds ratio 2.3, 95 percent confidence interval 1.1 to 5.1 — after adjusting for peripheral neuropathy and retinopathy. Even more striking: once vestibular dysfunction, peripheral neuropathy, and retinopathy (eye damage) were all entered into the model together, the association between diabetes itself and falling disappeared. The three complications explained it.
Read that plainly. In a diabetic patient, testing the feet and stopping there measures part of the risk and calls it the whole. Peripheral neuropathy is independently associated with falls in its own right. A 2024 case-cohort study in the Journal of the Peripheral Nervous System found the same — but that study followed only 31 people. Read its effect size as a direction, not a number to quote.
No one of these is a fall-risk score. Together they say which system is failing, by how much, and whether we can treat it.
VNG — the inner ear and its links to the brain. It separates an inner-ear loss, which often responds to rehab, from a brain pattern that means something else is going on.
Cognivue [Cognitive and Memory Testing] — a computer test of thinking and memory. Attention and processing speed let you react to a trip before you hit the floor. That is exactly why thinking tests are a named part of a standard fall-risk check.
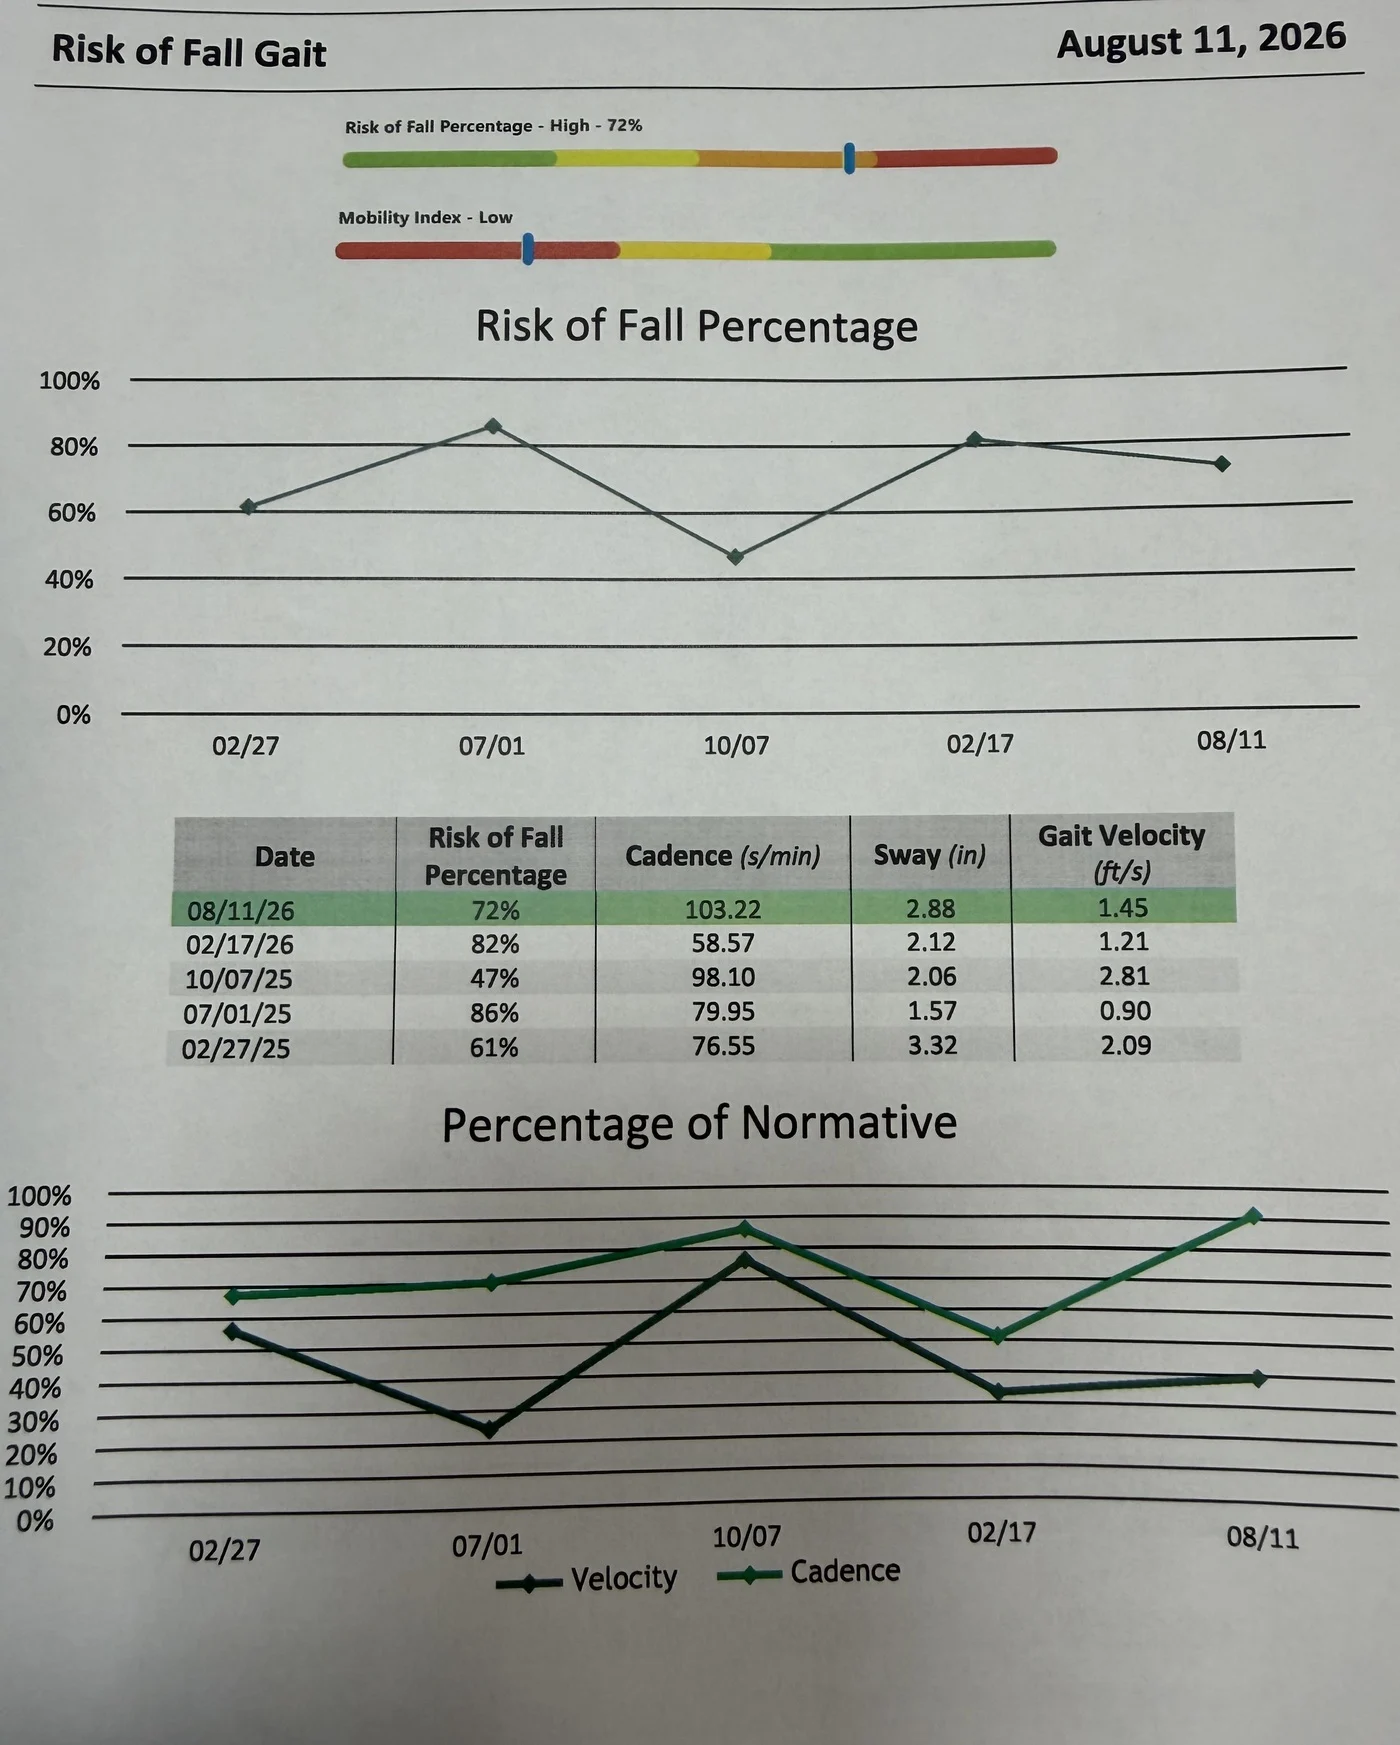
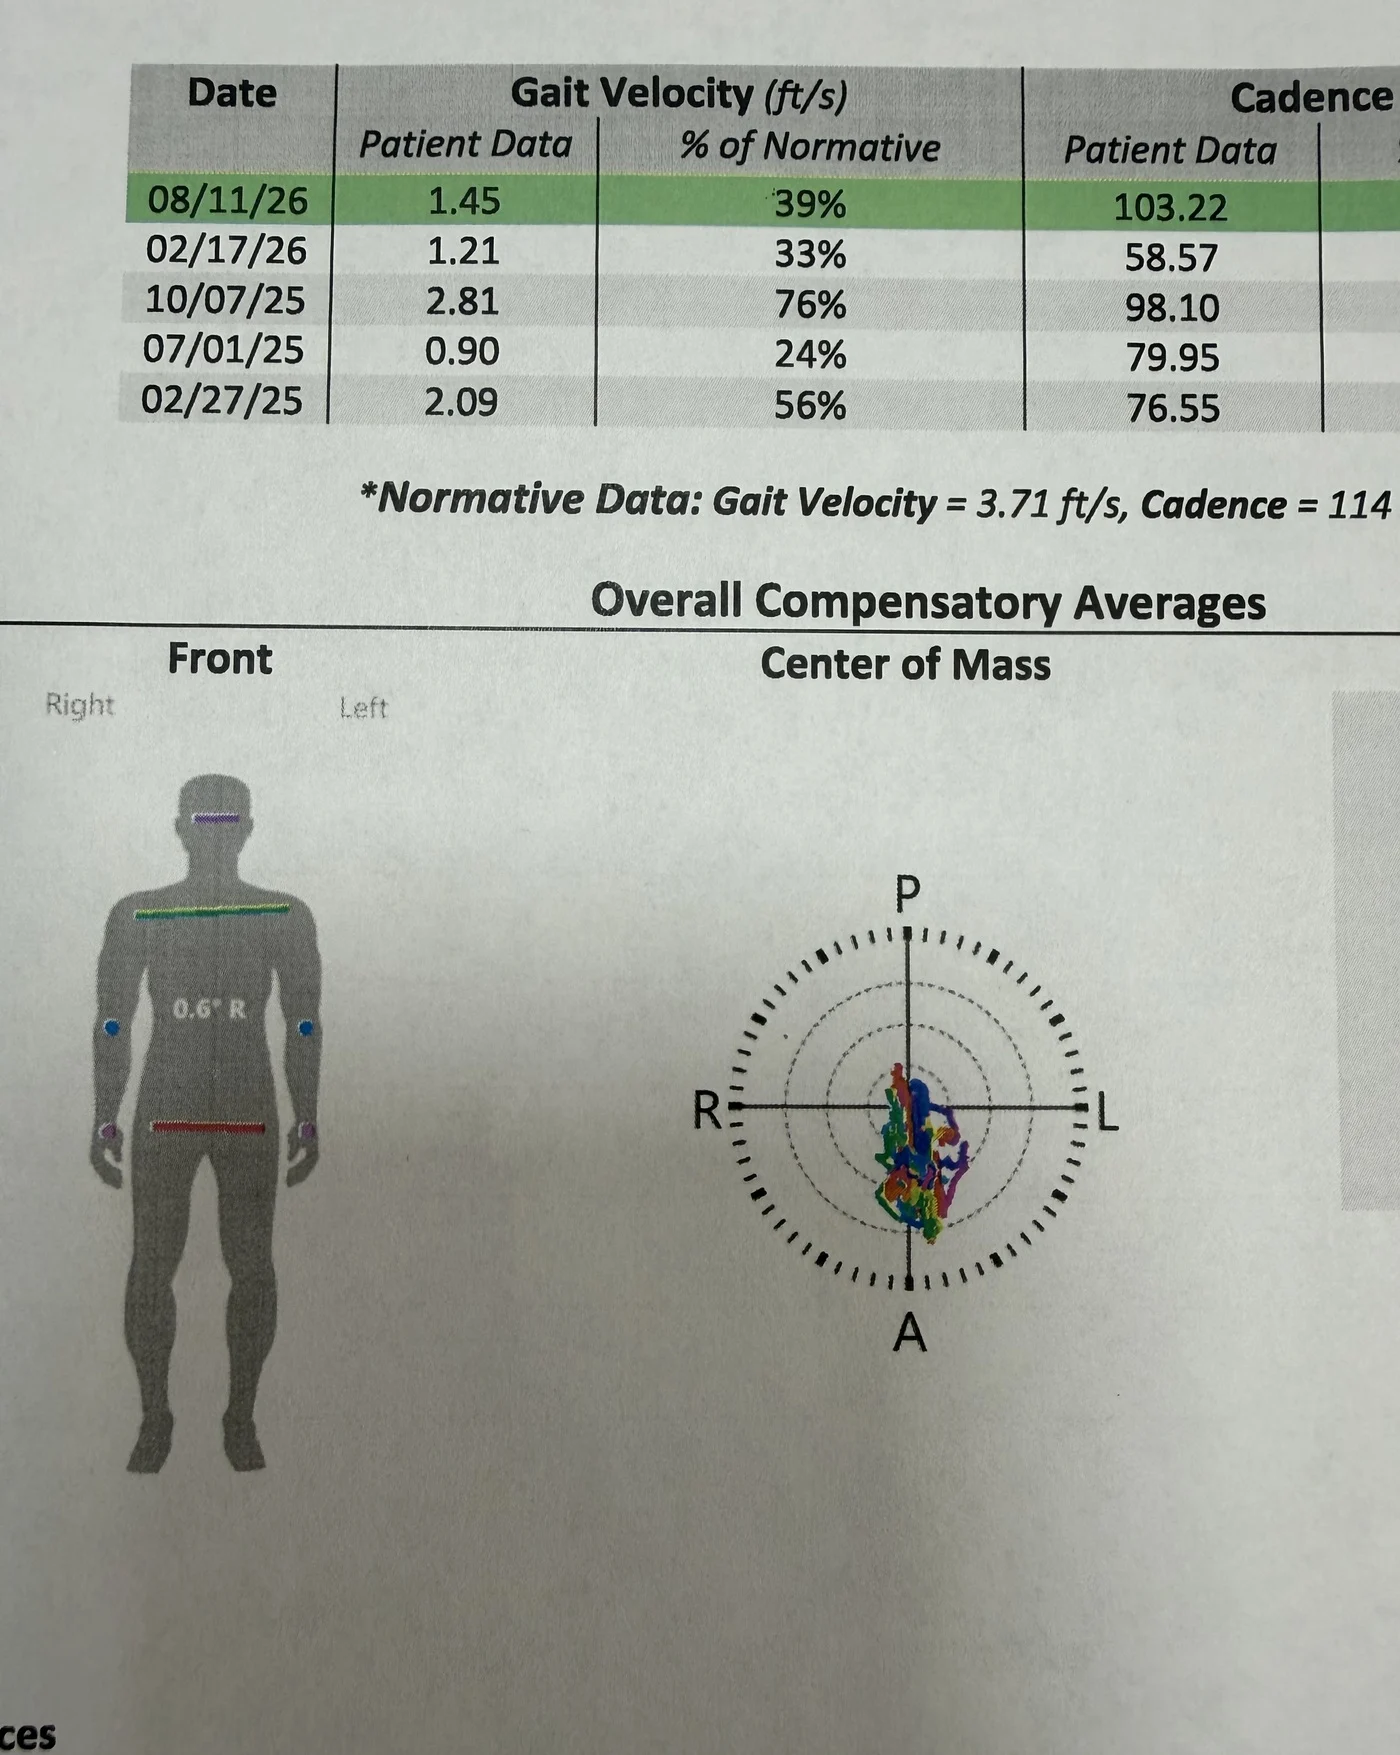
Kinetisense [Gait Analysis for Fall Analysis] — markerless motion capture that records how you really move. It tracks gait, posture, weight shift, and how you rise from a chair. It measures the output of the whole system, after all the covering is done.
Small fiber and autonomic testing — the small nerve fibers that carry feeling from the sole, and the autonomic fibers (the automatic nerves) that hold your blood pressure up when you stand. Blood pressure that drops when you stand is a cause of falls on its own, and it is silent.
Ankle–brachial index and peripheral vascular flow — because numb, cold, painful feet are not always nerve. Blood flow and nerve cause similar symptoms but need totally different treatment.
EMG and nerve conduction studies — where the weakness is coming from. A foot that will not clear the ground can be a nerve in the leg, a nerve root at the spine, or muscle. Nerve testing tells them apart. The answer changes what is worth treating.


Every system above can fail quietly. Every one can be covered for — until another one fails. That is the trap. Someone can lose most of one inner ear and walk fine in a bright, familiar room. Then they go down in a dark hallway or on a patterned carpet, where vision stops helping.
A single test finds a single problem. It tells you nothing about the reserve behind it. Measuring several systems tells you how many still work. That is what predicts whether the next stumble ends on the floor. The research on balance testing lands in the same place from the other side. A systematic review of balance tests found a brief test is fine for screening. But a full set of tests is needed for a complete assessment.
It also gives you something a score cannot: a list of which problems can be treated. Inner-ear loss can be retrained. Blood pressure drops on standing can be managed. A medicine that adds to the risk can be rethought. A pinched nerve root can be treated. Knowing which of those is in play is the whole point.
You will sit for the VNG part, wearing a light headset with sensors around the eyes. You will follow a moving target with your eyes. Your head and body will be moved into several positions. Part of the recording is done with your eyes open in the dark. That is when the inner ear has to work without vision covering for it.
Some position changes can bring on brief dizziness. That is not a side effect. Bringing it on and recording it is how the test finds the problem. It usually settles within minutes of sitting up. Bring someone to drive you if you get motion sick or if dizziness is your main symptom.
The other parts are painless. Cognivue [Cognitive and Memory Testing] is done at a screen. Kinetisense [Gait Analysis for Fall Analysis] records you walking and standing. Blood flow and autonomic tests use cuffs and stick-on pads. Nerve conduction studies use brief electrical pulses that feel like a tap or a snap. Needle EMG, when needed, uses a fine solid needle. Most patients call it a deep ache, not a sharp pain.
Tell us ahead of time what you take. Several medicines will change the recording. That includes sedatives, some antihistamines, and anything that blocks dizziness. We will tell you which to hold and for how long.
The result is a map of which systems are adding to the problem, and by how much. That drives four decisions.
What can be retrained — an inner-ear loss often can, and the exercises match which side and which canal. What is medical — a blood pressure drop on standing, low B12 or vitamin D, or blood sugar doing damage below the line that gets called diabetes. What is structural — a nerve root or a stenosis that nerve testing has pinned down. And what is in your surroundings. If you are running on vision, then lighting, floors and shoes stop being lifestyle tips. They become part of the treatment.
We also repeat the test. The results are numbers, and they can be repeated. That is what makes testing over time worth doing. A gait test returns a risk-of-fall percentage, a mobility score, step rate, sway and walking speed. Each is also shown against normal values. Read once, it is a snapshot. Read across visits, it shows whether the direction has changed — and whether what we did moved anything.
Nerve, vessel, inner ear, and brain are not four unrelated organs that just happen to fail together. They share a blood supply, and they share the same ground. Small vessels and small nerve fibers are the first tissue to feel a metabolic problem. They are the last to be checked. That is why a person can be told their labs are fine while three balance systems are already breaking down.
The survey data make this concrete, not theory. In the National Health and Nutrition Examination Survey, vestibular dysfunction in people with diabetes was not just present or absent. It tracked with how long they had been diabetic and with their hemoglobin A1c (average blood sugar). The authors said this pattern suggests a dose–response link: the worse the metabolic disease, the worse the damage to the inner ear. The ear was reading the metabolic state, the same way the feet were.
That is why this test does not stop at the balance organs. We also check blood sugar handling, insulin resistance, B12 and vitamin D, blood pressure control, muscle mass, and blood flow. Those are the upstream drivers of what the balance tests measure downstream. Insulin resistance shows up years before a diabetes diagnosis, and a routine glucose test will miss it. Metformin drains B12. Losing muscle takes away the strength to catch yourself. It also takes away a source of the signal molecules that control inflammation.
Treating the readout without treating the terrain buys a little time. Treating the terrain is what changes direction.
A fall-risk test sounds like a narrow, technical thing. It is not. Here is plainly why we put this much into it.
Falling is rarely a single event. It is the hinge in a chain. An injury, then fear of falling, then less walking, then less muscle. Then worse blood sugar, worse blood flow, worse nerves, worse balance — and a higher chance of the next fall. Each turn of that loop also takes something a person cares about. Driving. Stairs. Showering without help. Going out after dark. Living in their own home. People stop doing these one at a time, usually without telling anyone. The medical system tends not to notice until an ambulance shows up.
The cost does not stay with one person either. It lands on a spouse who becomes a caregiver. It lands on grown children who rework their jobs. It lands on a health system that pays for the broken hip and the rehab, but not for the test that would have found the loose part eighteen months earlier. One person’s decline is not private. It spreads onto everyone around them.
That is why we test across fields. We do not send the ear to one specialist, the feet to another, and the memory to a third. Each of them sees a normal result in their own lane and sends the patient on. The way the systems interact is the finding. Nobody looking at one system alone can see it.
Anyone with peripheral neuropathy, especially diabetic neuropathy. Anyone who has had a fall or a near-fall in the past year. Anyone who has stopped doing something — stairs, showers without a rail, walking outside after dark — because of unsteadiness, not pain. Anyone with dizziness, lightheadedness on standing, or an off-balance feeling that has never been sorted out.
Also anyone with a long medicine list, if nobody has asked lately what the whole list does to their balance. That is its own review, and it is worth having.
You do not need a referral to be evaluated here.

Balance, feeling, blood flow, thinking and nerve function are measured together, because a single test cannot tell you how much reserve you have left.
Same-day appointments are often available. No referral is required.
Prefer not to fill in a form?
Same-day and emergency appointments are available.
Part of our complete guide to Interventional Pain Management in St. Louis.