Lateral hip pain labeled trochanteric bursitis is usually greater trochanteric pain syndrome. The gluteal (buttock) tendons attach at the greater trochanter, the bony knob on the outer hip. Those tendons handle load poorly. The bursa is rarely the whole story. In a systematic review of more than 950 cases, a steroid shot (corticosteroid injection) cleared symptoms in 49% to 100%,1 a wide range built mostly on level IV evidence.
Trochanteric bursitis is often treated like a simple “side-hip inflammation” problem. But the condition we actually see is broader than that. Many people get stuck on the assembly line, and nobody closes the loop. One systematic review of trochanteric bursitis covered more than 950 cases. Clearing of symptoms and return to activity ranged from 49% to 100% with corticosteroid injection as the main treatment, with or without other non-surgical care.1 Most of the studies were level IV evidence. So read that range as wide for a reason, not as a precise success rate.
What Causes Lateral Hip Pain That Gets Labeled “Trochanteric Bursitis”
Here is the honest framing. Many patients come in with a referral diagnosis of “trochanteric bursitis,” but what we often treat is GTPS, a pain syndrome involving the greater trochanter region where the gluteal tendons attach. Those tissues handle load poorly.
The “bursa” word is sticky, but in 2026 we are more careful about mechanism. The pain is usually amplified by abnormal tendon loading, local tissue irritation, and sometimes other factors that add to it. These include hip mechanics, weak muscles and changes in how you walk. Does it also act on nerve endings inside the bone? That is a hypothesis, not an established mechanism.
Because of that, treatment that only targets “inflammation” without changing load and mechanics often falls short. We can reduce pain. But if the mechanical driver stays, central sensitization (a nervous system stuck on high alert) persists.
Common pain patterns patients describe
- Side-lying pain, above all when pressure hits the lateral hip.
- Point tenderness over the greater trochanter.
- Pain with stairs, getting in and out of a car, or long walks.
- Symptoms that may come and go but mostly track with load.
Important mimics (why your diagnosis needs to be defended)
Diagnosis is mainly clinical. That means it rests on your history and exam. But scans are often used to rule out other causes of lateral hip pain. These include osteoarthritis, femoroacetabular impingement, lumbar spondylosis, hernias, and avascular necrosis of the femoral head.
In plain terms: maybe your pain does not act like an outer hip problem that flares with load. Then the plan should not assume it is GTPS just because it hurts near the trochanter.
How Is Trochanteric Bursitis Diagnosed?
The defensible position is this. If you do not look like GTPS on exam, injections or other procedures have not been shown to help you reliably. That is why diagnosis is not a single yes or no.
We start with history and exam. Then we decide what imaging is needed to reduce doubt about the diagnosis. Maybe you came from a pathway that only did an X-ray and called it a day. If so, you may have missed the part that matters: the targeted clinical pattern.
Clinical exam elements that drive the plan
- Tenderness when we press on the greater trochanter.
- Test moves that bring back your lateral hip pain.
- Checks of hip strength, control and walking pattern (gait).
- A screen for spine or hip joint problems when your history points there.
Imaging: when it clarifies, when it misleads
- Often useful: MRI or ultrasound when tendon damage is suspected or when symptoms are unusual.
- Sometimes misleading: incidental findings can show up in people who do not have that pain source.
- Goal: rule out other causes, not “find something” to justify any procedure.
If you want to see how we structure the first visit, use this guide to what happens at a first appointment.
Shockwave Therapy, Physical Therapy, and Stacking Treatments
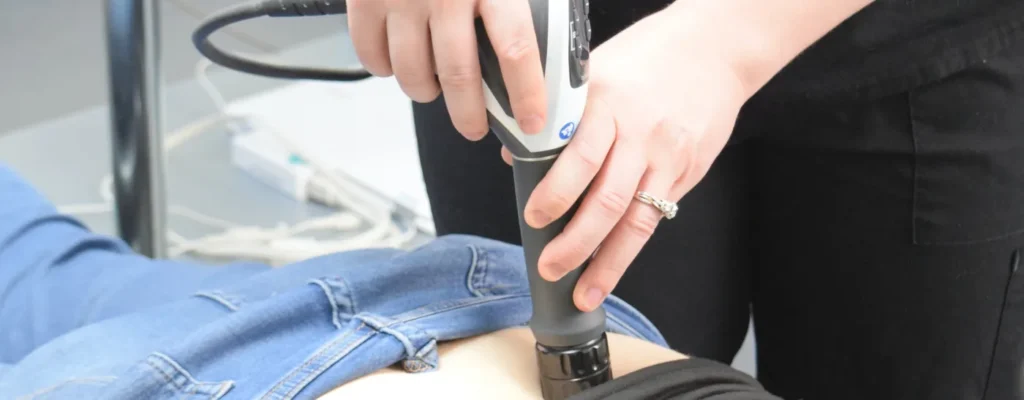
Shockwave therapy is one option patients ask about. They want trochanteric bursitis treatment that avoids injections or cuts how often they are needed.
That same systematic review looked at two head-to-head studies. Both found low-energy shockwave therapy beat other nonsurgical care for stubborn cases.1 That does not mean every patient improves, and the comparative evidence is limited. But it does mean the signal is not imaginary.
Does PT help, or is it just a box to tick?
Physical therapy with corticosteroid injection appears to work better for new, acute symptoms than physical therapy alone. That makes sense. But the real question is whether your PT is actually specific and progressive.
How we sequence care
- First: calm the irritated tissue and remove obvious overload.
- Second: build capacity with a strengthening and movement plan you can measure.
- Third: consider injection or shockwave if you are not progressing or if the diagnosis is mixed.
If your case overlaps with broader patterns of chronic pain, the “mechanical only” approach can fail. Acceptance and Commitment Therapy chronic pain strategies can help. They help patients stop wrestling with pain signals that now act like a false alarm.
We are not saying psychology replaces tendon care. We are saying it fixes the central sensitization that pain creates.
Frequently asked questions
What is the best trochanteric bursitis treatment if I cannot stop walking for work?
Maybe you cannot fully stop activity. Then the best start is usually to change your activities to cut direct pressure. Add a specific hip strengthening program. If pain blocks progress, a targeted corticosteroid injection may be used as a bridge. But it only makes sense when your exam and history fit GTPS. See hip joint injection for how this is evaluated.
Is shockwave therapy worth it for trochanteric bursitis?
In 2026, shockwave therapy is a reasonable option for selected GTPS patients. Reviewed evidence reports meaningful improvement in pain scores versus control groups. It is not a fix for everyone. It works best when paired with progressive PT, so symptoms do not return as soon as you load the tendon again. See image-guided procedures for how this is evaluated.
Do I need imaging to confirm trochanteric bursitis, or is clinical diagnosis enough?
Diagnosis for GTPS is mainly clinical, and imaging is often used to rule out other causes of lateral hip pain. Imaging matters more if your symptoms are unusual, getting worse, or not responding to a well-built plan. It protects you from the wrong treatment. See trigger point injections for how this is evaluated.
Can trochanteric bursitis feel like sciatica, and should I pursue sciatica treatment instead?
Sometimes lateral hip pain overlaps with pain referred from the back, so it can feel like sciatica. We do not switch to sciatica treatment without an exam. That exam checks whether the pain source is lateral hip GTPS or a nerve problem. See shockwave therapy for how this is evaluated.
How long does it usually take to improve with trochanteric bursitis?
With proper care, many people start to improve within six to 10 weeks. That is most true when strengthening and load management are done correctly. If you are still stuck at month four with no gains in function, the honest move is a re-evaluation. Do not just repeat the same trochanter-directed care. See hydrodissection for how this is evaluated.
To discuss your own case, request an appointment through the appointment request form, call (314) 481-5000, or text (314) 886-5902. You can review the full range of pain treatments, read about the pain management doctors in St. Louis, or find both offices on the locations page.
Sources
- Lustenberger DP, Ng VY, Best TM, Ellis TJ. “Efficacy of treatment of trochanteric bursitis: a systematic review.” Clinical Journal of Sport Medicine, 2011;21(5):447–453. 24 articles, more than 950 cases; most were level IV evidence. doi:10.1097/JSM.0b013e318221299c
Dr. Gurpreet Singh Padda, MD, MBA, MHP


