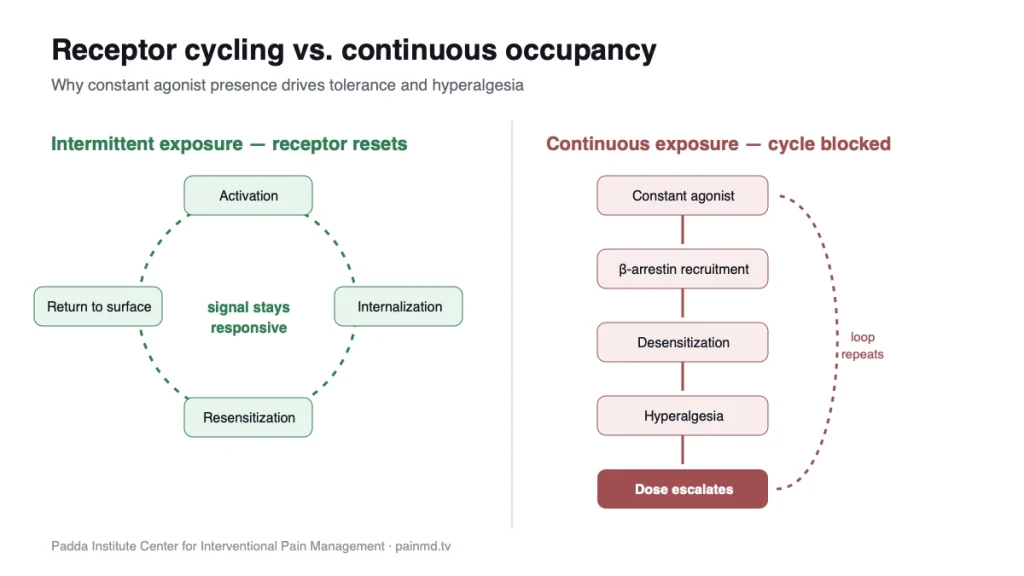
Long-acting opioids make pain worse by keeping the mu-opioid receptor occupied around the clock. So it never resets to full sensitivity. The receptor wears down and cuts out. The result is opioid-induced hyperalgesia: pain climbs as the dose climbs.
There is a quiet paradox in chronic pain care. The patient’s dose keeps climbing while the pain keeps getting worse. It is usually read as a worsening disease or drug-seeking. Often it is neither. It is the drug doing what it does when a receptor never gets to rest.
Why does the opioid receptor need to reset?
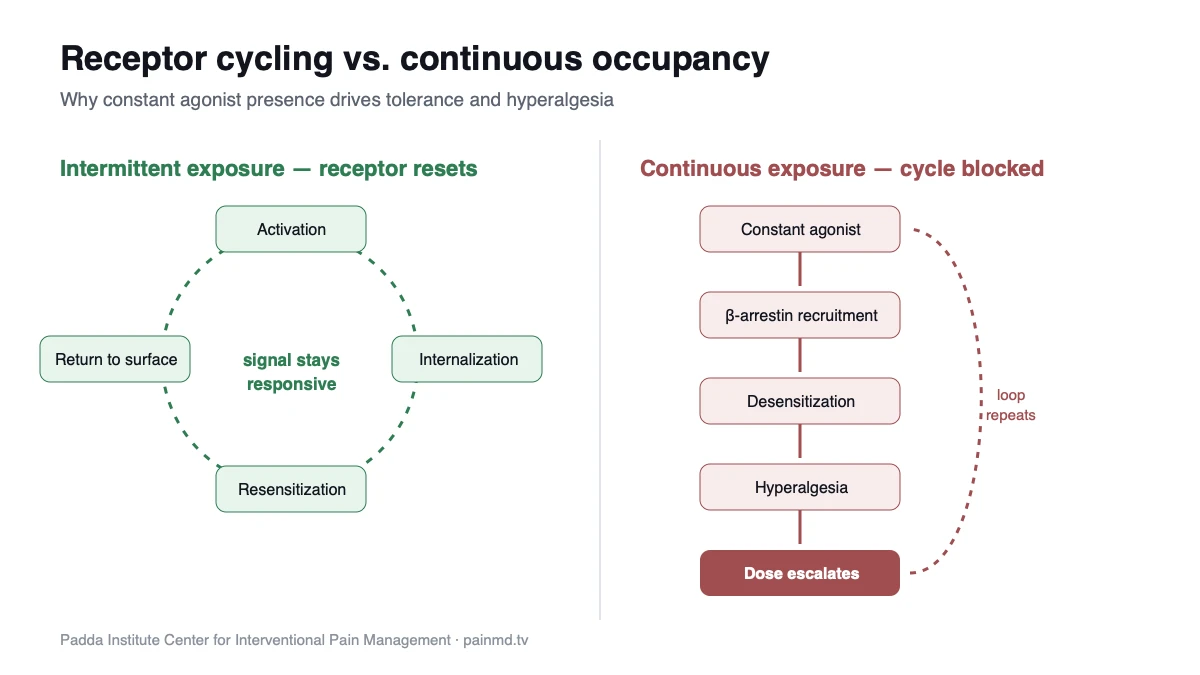
The mu-opioid receptor is a G-protein-coupled receptor. It is controlled by tagging its tail with phosphate. That draws in beta-arrestin proteins, which pull the receptor into the cell. The cycle goes like this: switch on, pull inside, reset, return to the surface. It is not a defect. It is how the system stays responsive.
When a drug is always on the receptor, the loop cannot finish. The receptor wears down and disconnects. The signal it was built to carry fades.
How can opioids make pain worse?
The end result is opioid-induced hyperalgesia. Pain sensitivity rises even as doses go up. The patient hurts more, so the dose rises. So the receptor is occupied more of the time. So sensitivity rises further.
Alongside it runs central sensitization: the nervous system amplifying signals it once filtered out. The pain relief shrinks while the pain itself gets worse.
Why are long-acting opioids harder on the nervous system than short-acting ones?
Short-acting and long-acting opioids are not just different schedules of the same drug. Long-acting drugs keep the receptor occupied almost nonstop. In doing so, they deny the nervous system the drug-free rest it needs to reset and rebalance.
Constant outside stimulation also shuts down the body’s own endorphins and enkephalins (natural painkillers). The built-in system stops responding to natural triggers like stress or exercise. Patients lose their built-in ability to ease pain and steady mood. The best name for this is physiological insolvency. The outside supply loses power while the inside supply runs dry.
The pill-count paradox
Here is where clinical reality collides with metrics. Enforcement headlines quote raw pill counts. That pushes pharmacies to push for fewer pills. The easy way to cut the pill count is to switch a patient to longer-acting medicine. That looks better on paper. But it produces exactly the nonstop receptor occupancy described above.
A lower pill count is not the same as a lower risk. We defend more pills at a truly low total dose. A tidier number bought by flooding the receptor is worse. Our full protocol is set out for pharmacy partners in our opioid stewardship guide.
What does Padda Institute do instead?
We treat pain with a program of procedures and metabolic care, and when opioids are used at all, they sit inside that program rather than standing alone. We keep working to lower the dose. It is usually under 30–40 MME (morphine milligram equivalents). The average is nearer 27–32.5 MME.
Patients usually arrive on more than 90 MME per day. Most have been in pain for more than two and a half years. Within 90 days of active treatment with procedures, 21% are fully off opioid pain medicine. Within one year, 34% are fully off all opioid pain medicine. Of those who cannot fully come off, the large majority are brought below 30 MME per day. The full breakdown is in our pill counts vs. pharmacology discussion. These are practice-reported figures from our own patients, not trial results, and individual results vary. They were published on International Overdose Awareness Day, August 31, 2026 — see the announcement.
Rebuilding the body’s own system matters as much as cutting the outside supply. Sleep and body-clock health are central to that. Deep sleep is when the body recharges its own pain relief. See circadian rhythm disruption and chronic pain and artificial light at night.
Frequently asked questions
What is opioid-induced hyperalgesia?
It is a backward state where pain sensitivity rises even as opioid doses go up. It happens when nonstop receptor occupancy wears down and disconnects the mu-opioid receptor. So the same or a higher dose gives less relief and more sensitivity. Individual results vary.
For how hyperalgesia is told apart from tolerance and a worsening condition, read Is Your Pain Medication Making Your Pain Worse?
Does this mean opioids are always harmful?
No. Opioids have a real role, especially in sudden pain, cancer pain and pain around surgery. The concern is long-term, nonstop exposure with no plan to lower it. That goes double for long-acting forms that never let the receptor reset. Do not start, stop, or change any prescribed medication on your own — that decision belongs with your physician.
For the outcome data on long-acting formulations, read Pill Counts vs. Pharmacology: What Pharmacists and Referring Physicians Should Know.
If my pill count went down, isn’t that safer?
Not always. Pill count and drug risk are different measures. Switching to longer-acting drugs lowers the pill count. But it keeps the receptor occupied more of the time. Total morphine-equivalent dose and the pattern of exposure matter more than the number of pills.
Why does my pain get worse even though my opioid dose keeps going up?
It is usually read as a worsening disease or as drug-seeking. Often it is neither. Say the mu-opioid receptor is occupied around the clock. It wears down. It stops carrying the signal well. Pain sensitivity rises, and the dose rises to chase it. The nervous system starts amplifying signals it once filtered out. More medicine buys less relief.
Do long-acting opioids lower your natural endorphins?
Yes. Constant outside stimulation shuts down the body’s own endorphins and enkephalins. So the built-in system responds less to natural triggers such as stress or exercise. You lose your built-in ability to ease pain and steady mood. The best name for this is physiological insolvency. The outside supply weakens while the inside supply runs down.
Will Padda Institute manage my pain with medication alone?
No. When opioids are used at all, they sit inside a program of procedures and metabolic care. We keep working to lower the dose. Rebuilding the body’s own pain control matters as much as cutting the outside supply. That is why sleep and body-clock health are part of the plan.
Where are you located and how do I make an appointment?
Padda Institute Center for Interventional Pain Management, 4477 Woodson Rd, Suite 100, St. Louis, MO 63134. Book at painmd.tv/appointment/ or call (314) 481-5000.
Addresses, hours and directions are listed on our Locations page.
Key takeaways
- The mu-opioid receptor depends on a cycle of being pulled inside and reset to stay responsive.
- A drug that is always present wears the receptor down. That feeds opioid-induced hyperalgesia.
- Long-acting forms deny the nervous system the rest that cycle needs.
- Long-term use also shuts down the body’s own endorphins — a state of physiological insolvency.
This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not start, stop, or change any medication without consulting your physician.
References
Ray 2016 and Miller 2015 are observational and cannot exclude confounding by indication; Birdsong 2015 is cellular work describing a receptor mechanism, not a clinical outcome. Reference 8 is included as counter-evidence.
- Birdsong WT, Arttamangkul S, Bunzow JR, Williams JT. Agonist binding and desensitization of the μ-opioid receptor is modulated by phosphorylation of the C-terminal tail domain. Mol Pharmacol. 2015 Oct;88(4):816–24. PMID 25934731.
- Angst MS, Clark JD. Opioid-induced hyperalgesia: a qualitative systematic review. Anesthesiology. 2006 Mar;104(3):570–87. PMID 16508405.
- Higgins C, Smith BH, Matthews K. Evidence of opioid-induced hyperalgesia in clinical populations after chronic opioid exposure: a systematic review and meta-analysis. Br J Anaesth. 2019 Jun;122(6):e114–e126. PMID 30915985.
- Mercadante S, Arcuri E, Santoni A. Opioid-induced tolerance and hyperalgesia. CNS Drugs. 2019 Oct;33(10):943–55. PMID 31578704.
- Clauw D. Hijacking the endogenous opioid system to treat pain: who thought it would be so complicated? Pain. 2017 Dec;158(12):2283–4. PMID 28957836. (Editorial.)
- Ray WA, Chung CP, Murray KT, Hall K, Stein CM. Prescription of long-acting opioids and mortality in patients with chronic noncancer pain. JAMA. 2016 Jun 14;315(22):2415–23. PMID 27299617.
- Miller M, Barber CW, Leatherman S, Fonda J, Hermos JA, Cho K. Prescription opioid duration of action and the risk of unintentional overdose among patients receiving opioid therapy. JAMA Intern Med. 2015 Apr;175(4):608–15. PMID 25686208.
- Chu LF, D’Arcy N, Brady C, et al. Analgesic tolerance without demonstrable opioid-induced hyperalgesia: a double-blinded, randomized, placebo-controlled trial of sustained-release morphine for chronic nonradicular low-back pain. Pain. 2012 Aug;153(8):1583–92. PMID 22704854. Counter-evidence — found tolerance without demonstrable hyperalgesia.
Find the source of your pain — not just the signal
Padda Institute Center for Interventional Pain Management builds a custom, root-cause plan for each patient. Interventional care and metabolic medicine, under one roof in St. Louis.
Or call or text us — 4477 Woodson Rd, Suite 100, St. Louis, MO 63134.
Msg & data rates may apply. Reply STOP to opt out, HELP for help. Text is not a secure channel — please don’t send medical or personal health information by text, and don’t use text for emergencies.
Opioid stewardship & pain neurobiology
- Is your pain medication making your pain worse?
- Opioid bankruptcy: why opioids stop working
- Pill counts vs. pharmacology: what pharmacists should know
- Why long-acting opioids can make pain worse
- Opioid stewardship: what pharmacists and referring physicians should know
Medically reviewed by Dr. Gurpreet Singh Padda, MD, MBA, MHP — Board Certified in Anesthesiology, Pain Medicine, Interventional Pain Management, Addiction Medicine, and Obesity Medicine. Last reviewed July 2026.
Dr. Gurpreet Singh Padda, MD, MBA, MHP


